Inadequate Spinal Anesthesia Rates and Associated Factors
Inadequate neuraxial anesthesia affects 4.9% of adult patients undergoing cesarean deliveries under planned spinal anesthesia, according to a retrospective cohort study. Conducted at a tertiary university hospital between January 2020 and January 2026, the study analyzed 3,382 cesarean deliveries. Out of the total procedures evaluated, adequate surgical anesthesia was successfully achieved in 3,216 patients, while 166 patients experienced inadequate anesthesia, which researchers defined as a combination of partial and total failures.
The study broke down these failures into specific clinical outcomes, identifying 135 partial failures, which accounted for 4.0% of the cohort, and 31 total failures, representing 0.9% of the cases. A separate scoping review noted that the reported incidence of inadequate neuraxial blocks across various literature sources ranges from 0% to 27%, reflecting wide inconsistencies in how different institutions define and track block failures.
Independent Predictors of Spinal Block Failure
Multivariable logistic regression analysis revealed that both patient-related and surgical factors significantly alter the odds of experiencing inadequate spinal anesthesia. Increasing patient age and higher educational levels were associated with lower odds of block inadequacy. Conversely, specific clinical events such as postpartum sterilization and surgical adhesions were independently associated with higher odds of failed spinal anesthesia.
These findings build on previous clinical observations. A separate retrospective review of 5,361 cesarean deliveries similarly identified previous cesarean delivery, concomitant tubal ligation, lower body mass index, and longer surgery duration as predictors of failure in that cohort. However, researchers note that while these risk factors have been proposed, their relative predictive value in routine obstetric practice remains unclear.
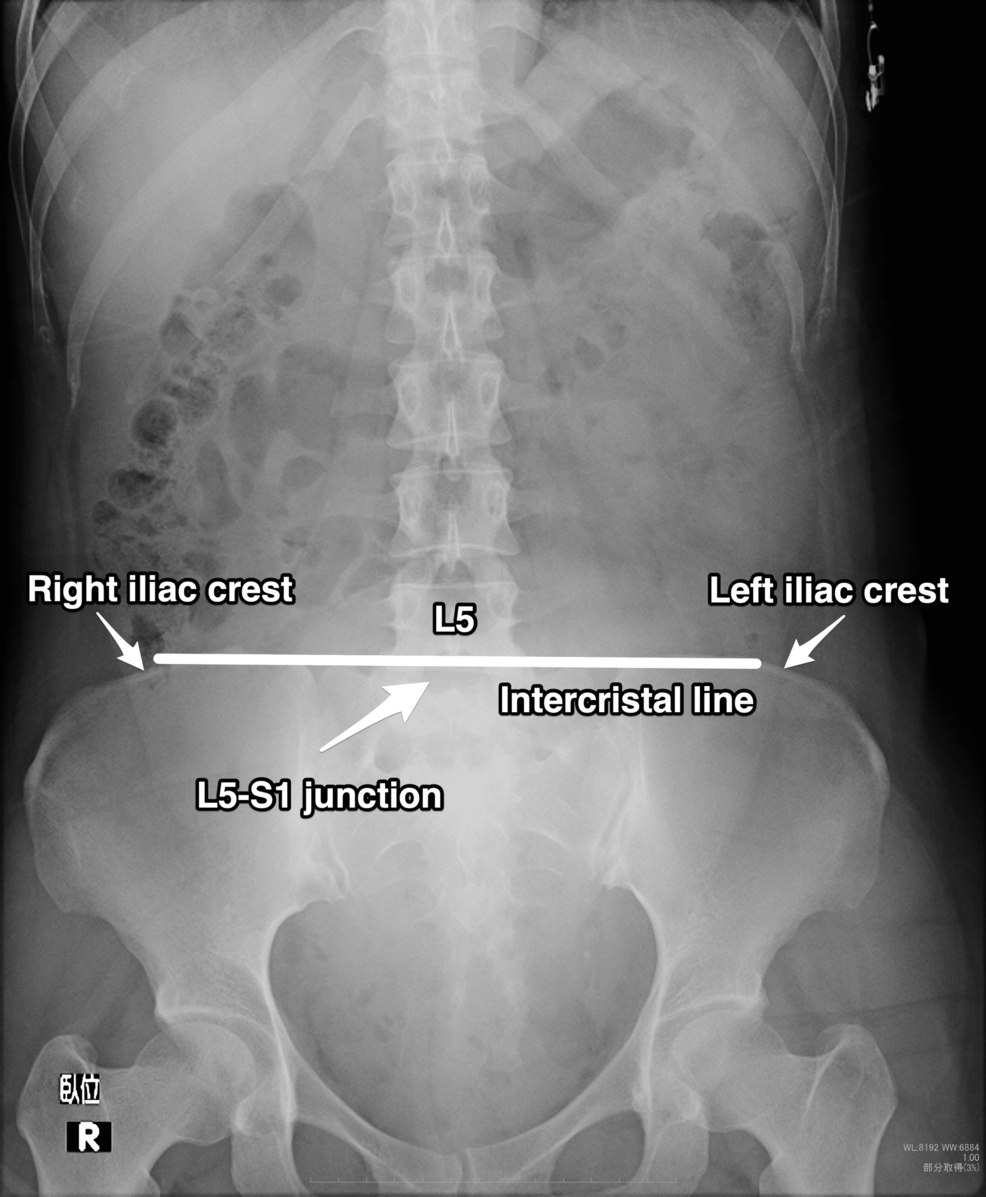
Beyond institutional cohort studies, detailed clinical case reviews highlight the anatomical challenges that clinicians face. A documented case report examined a patient who experienced inadequate spinal anesthesia during her first two cesarean deliveries. The report detailed how palpation-based identification of lumbar interspaces in term parturients can be inaccurate.
Clinical Management and Pharmacological Rescue Strategies
When spinal anesthesia fails to provide pain-free surgery, clinicians rely on a diverse array of rescue strategies to avoid emergency conversion to general anesthesia. A systematic scoping review evaluated emergency cesarean deliveries and found that intravenous opioids followed by S-ketamine were the most common pharmacological strategies used for supplementation when blocks proved inadequate.
Despite the use of these medications, their overall effectiveness remains unclear. The scoping review concluded that data regarding both patients’ and anesthesiologists’ experiences with inadequate neuraxial anesthesia remain sparse, and an absence of a consensus definition complicates efforts to track outcomes. Clinicians may experience difficulties identifying patients experiencing intraoperative pain, leading to variable rescue protocols.
For planned subsequent deliveries in patients with a history of failed blocks, individualized preparation can alter outcomes. In the case report, medical teams developed a structured anesthetic plan ahead of a third cesarean delivery. By reviewing previous anesthetic records, reassessing lumbar anatomy with ultrasonography, and defining rescue options in advance, the patient achieved successful surgical anesthesia using a dose of hyperbaric bupivacaine and fentanyl without requiring supplemental intravenous sedatives or general anesthesia.
Keep reading