Post-Tavr Complications Reveal Overlapping Bleeding and Clotting Disorders
A 67-year-old male patient who underwent a transcatheter aortic valve replacement experienced a severe drop in blood platelets driven by two distinct drug-induced mechanisms, Cureus reported. The case highlights the clinical challenges of managing overlapping prothrombotic and hemorrhagic conditions in hospitalized cardiac patients.
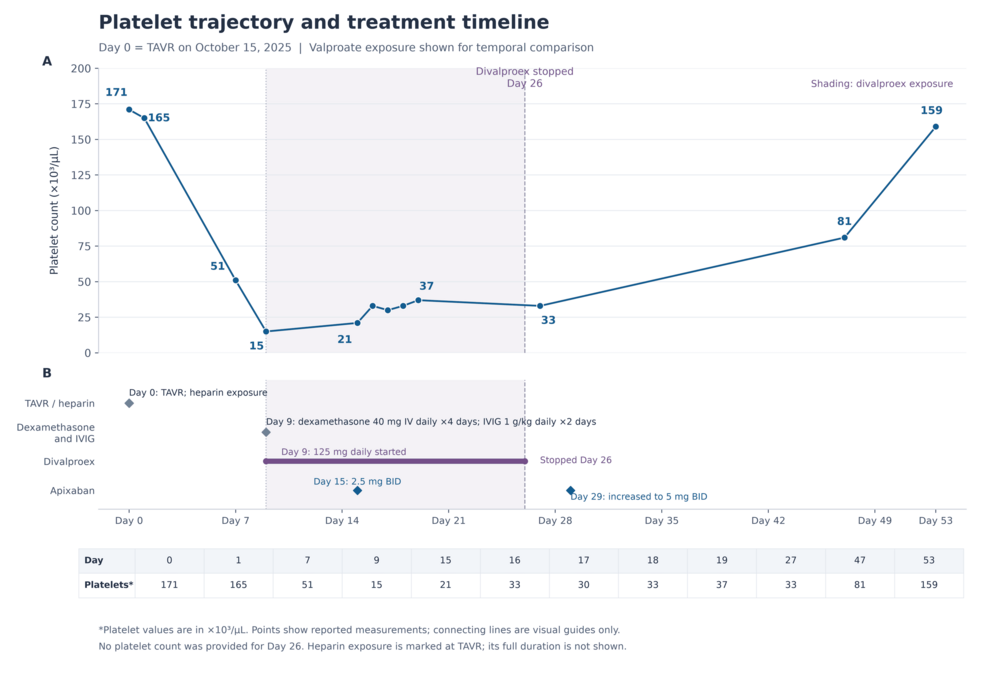
Following his procedure on Day 0, the patient presented on Day 7 with acute altered mental status and behavioral changes. Initial laboratory tests revealed his platelet count had fallen from a baseline of 165,000 per microliter to 51,000 per microliter. During his initial valve replacement admission, he received intraprocedural unfractionated heparin, though no further heparin products were administered. A 4Ts score of 5 indicated an intermediate probability for heparin-induced thrombocytopenia.
Diagnostic Workup and Treatment Challenges Following Heart Valve Surgery
To address postoperative delirium and agitation, clinicians initiated divalproex sodium at 125 milligrams daily on Day 9. Because physicians initially suspected immune thrombocytopenia in the absence of documented deep vein thrombosis on bilateral lower-extremity venous duplex ultrasonography, they administered dexamethasone and intravenous immunoglobulin. However, the platelet response remained minimal.
Subsequent testing confirmed heparin-induced thrombocytopenia through a positive enzyme-linked immunosorbent assay with an optical density of 1.994 and a serotonin release assay showing 100% serotonin release. PMC documented a separate case involving a 78-year-old male who developed mechanical hemolytic anemia from a paravalvular leak alongside heparin-induced thrombocytopenia following transcatheter aortic valve replacement. In the Cureus case, the hematology team started the patient on apixaban to mitigate bleeding risks, while platelet counts slowly recovered only after divalproex sodium was discontinued.
Clinical Distinctions Between Heparin and Valproate Complications
Heparin-induced thrombocytopenia is an immune-mediated prothrombotic disorder driven by immunoglobulin G antibodies against platelet factor 4-heparin complexes, which often leads to life-threatening thrombosis despite low platelet counts. Conversely, valproate-induced thrombocytopenia operates as a dose-dependent, nonimmune process causing direct bone marrow suppression and impaired platelet production.
This patient experienced a prolonged recovery timeline and thrombocytopenia following transcatheter aortic valve replacement. The overlap of these conditions created a therapeutic paradox where clinicians had to balance the urgent need for non-heparin anticoagulation against the bleeding risks associated with severe platelet suppression and dysfunction.
Frequently Asked Questions About Drug-Induced Thrombocytopenia After Valve Replacement
What caused the severe platelet drop in this patient?
The patient suffered from confirmed heparin-induced thrombocytopenia, an immune reaction to the heparin used during his transcatheter aortic valve replacement, compounded by valproate-induced thrombocytopenia from medication started for postoperative delirium.
How did doctors confirm the heparin-induced thrombocytopenia diagnosis?
Clinicians confirmed the diagnosis using an enzyme-linked immunosorbent assay that yielded an optical density of 1.994 and a serotonin release assay that demonstrated 100% serotonin release.
What role did valproate play in the patient’s recovery?
Valproate contributed to bone marrow suppression and impaired platelet production. Platelet counts remained depressed until the divalproex sodium was discontinued, allowing recovery to progress alongside non-heparin anticoagulation with apixaban.
Keep reading