Xanthogranulomatous Osteomyelitis: Understanding a Rare Bone Tumor Mimic
In the field of orthopedic pathology, clinicians often encounter lesions that present significant diagnostic challenges. Among these, xanthogranulomatous osteomyelitis (XO) stands out as a rare, chronic inflammatory condition that frequently masquerades as a malignant bone tumor. Because its clinical and radiological presentation often overlaps with aggressive neoplasms, distinguishing XO from bone cancer is a critical step in patient management.
What is Xanthogranulomatous Osteomyelitis?
Xanthogranulomatous osteomyelitis is an uncommon form of chronic osteomyelitis characterized by the infiltration of lipid-laden macrophages, known as foam cells, within the bone tissue. Unlike typical bacterial osteomyelitis, which often presents with clear signs of infection such as fever or acute purulence, XO can be insidious. It often presents as a destructive bone lesion, leading to diagnostic confusion with primary bone tumors or metastatic disease.
The condition is rare enough that it is frequently misdiagnosed in initial assessments. Because it mimics the appearance of a tumor on imaging studies like X-rays or MRIs, patients may undergo unnecessary and invasive procedures if the diagnosis is not carefully considered by a multidisciplinary team.
Diagnostic Challenges and Mimicry
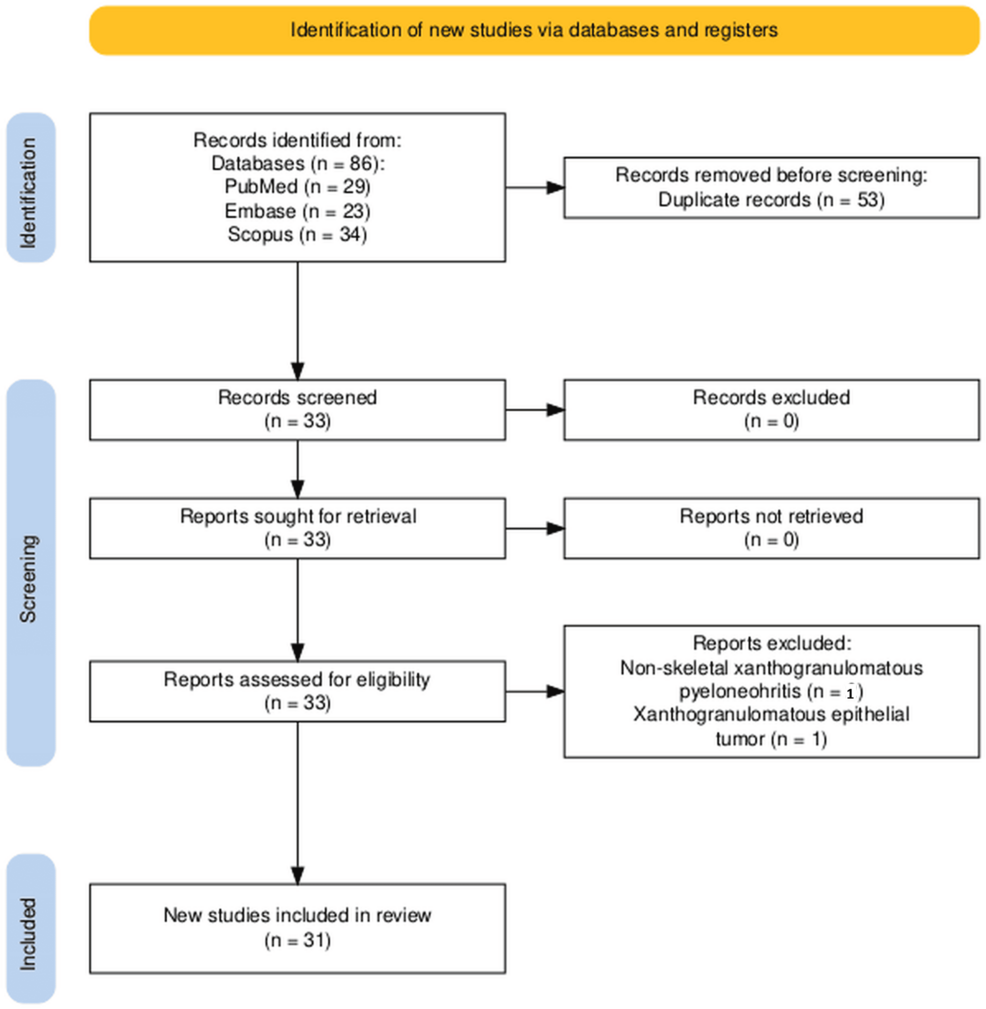
The primary hurdle in managing XO is its “tumor-mimic” nature. Imaging often reveals bone destruction, cortical thinning and soft tissue involvement—features typically associated with malignancy. According to a systematic review published in Cureus, identifying specific pre-biopsy diagnostic clues is essential for clinicians to avoid misdiagnosis.
Key clinical considerations include:
- Radiological Overlap: The lesion may appear as an aggressive, osteolytic process, which can lead practitioners to suspect sarcoma or metastatic cancer.
- Histopathological Findings: The definitive diagnosis relies on identifying the characteristic lipid-laden macrophages and chronic inflammatory cells through a biopsy.
- Differential Diagnosis: Clinicians must rule out other inflammatory conditions, fungal infections, and various bone tumors before settling on a treatment plan.
Management and Decision Points
Once XO is suspected, the management strategy shifts toward confirming the diagnosis while minimizing trauma to the affected site. Because the condition is inflammatory rather than neoplastic, the treatment approach is fundamentally different from that of a bone tumor.
The management of xanthogranulomatous osteomyelitis typically involves:
- Comprehensive Biopsy: Given the risk of misdiagnosis, a core needle or open biopsy is often required to obtain sufficient tissue for histopathological analysis.
- Multidisciplinary Consultation: Collaboration between orthopedic surgeons, radiologists, and pathologists is vital to interpret the imaging and biopsy results accurately.
- Targeted Therapy: While the specific treatment may vary based on the extent of the lesion, management often focuses on surgical debridement of the inflammatory tissue, sometimes followed by targeted medical therapy.
Key Takeaways for Patients and Clinicians
- Rare but Real: While XO is rare, it must remain in the differential diagnosis for any destructive bone lesion that does not fit the classic profile of a tumor.
- Biopsy is Essential: Never assume a destructive bone lesion is malignant without histopathological confirmation.
- Avoid Over-treatment: Accurate identification of XO can prevent radical surgeries that would be unnecessary for an inflammatory condition.
Conclusion
Xanthogranulomatous osteomyelitis remains a complex diagnostic puzzle. Its ability to mimic aggressive bone tumors highlights the importance of vigilance and the necessity of a systematic approach to diagnosis. By focusing on pre-biopsy clues and ensuring a thorough histopathological review, clinicians can provide more accurate diagnoses and avoid the morbidity associated with the incorrect treatment of benign inflammatory bone processes. As research continues to refine our understanding of this condition, improved diagnostic protocols will likely lead to better outcomes for patients facing these challenging bone lesions.

Disclaimer: This article is for informational purposes only and does not constitute medical advice. Always seek the guidance of your physician or other qualified health provider with any questions you may have regarding a medical condition.
- Understanding Childhood Cancer Treatment and Chemotherapy Success
- Ask Your Medical Science Questions to NPR
- Breakthrough Salk Study Uncovers Mechanism Behind Immunotherapy Resistance: Interferons, Mitochondrial Dysfunction, and PGE2″ Interferons, mitochondrial dysfunction and PGE2: Salk study reveals mechanism behind immunotherapy resistance. Boost its search engine visibility with relevant keywords for maximum impact. Immunotherapy resistance remains one of the biggest hurdles in cancer treatment. According to a recent study published in the journal Nature Communications, scientists at the Salk Institute have made a groundbreaking discovery that sheds light on the underlying mechanisms behind this resistance. The study reveals that interferons, a type of protein that plays a crucial role in the immune system, can contribute to mitochondrial dysfunction in cancer cells. This dysfunction can lead to the production of prostaglandin E2 (PGE2), a molecule that promotes tumor growth and resistance to immunotherapy. In their study, the researchers found that PGE2 production was a key factor in the development of immunotherapy resistance in cancer cells. The team used a combination of experimental and computational models to investigate the relationship between interferons, mitochondrial dysfunction, and PGE2 production. The findings of the study suggest that targeting PGE2 production could be a potential strategy for overcoming immunotherapy resistance. The researchers propose that blocking PGE2 receptors or inhibiting its production could help restore the function of mitochondria in cancer cells, making them more susceptible to immunotherapy. The study’s authors hope that their findings will pave the way for the development of new therapies that can overcome immunotherapy resistance and improve treatment outcomes for cancer patients. Key Takeaways: – Interferons contribute to mitochondrial dysfunction in cancer cells – Mitochondrial dysfunction leads to PGE2 production, promoting tumor growth and resistance to immunotherapy – Targeting PGE2 production could be a potential strategy for overcoming immunotherapy resistance – Restoring mitochondrial function in cancer cells could make them more susceptible to immunotherapy Keywords: immunotherapy resistance, interferons, mitochondrial dysfunction, PGE2, Salk Institute, cancer treatment, breakthrough study, Nature Communications. (archyworldys.com)