Diagnostic Mystery of Spontaneous Hernia
A 60-year-old woman suffering from worsening postprandial vomiting was initially diagnosed with dyspepsia and diaphragmatic eventration before doctors discovered a spontaneous left diaphragmatic hernia. Cureus reported that the patient experienced two years of recurrent epigastric pain radiating to her left back, early satiety, and a weight loss of 7 kg over two months.
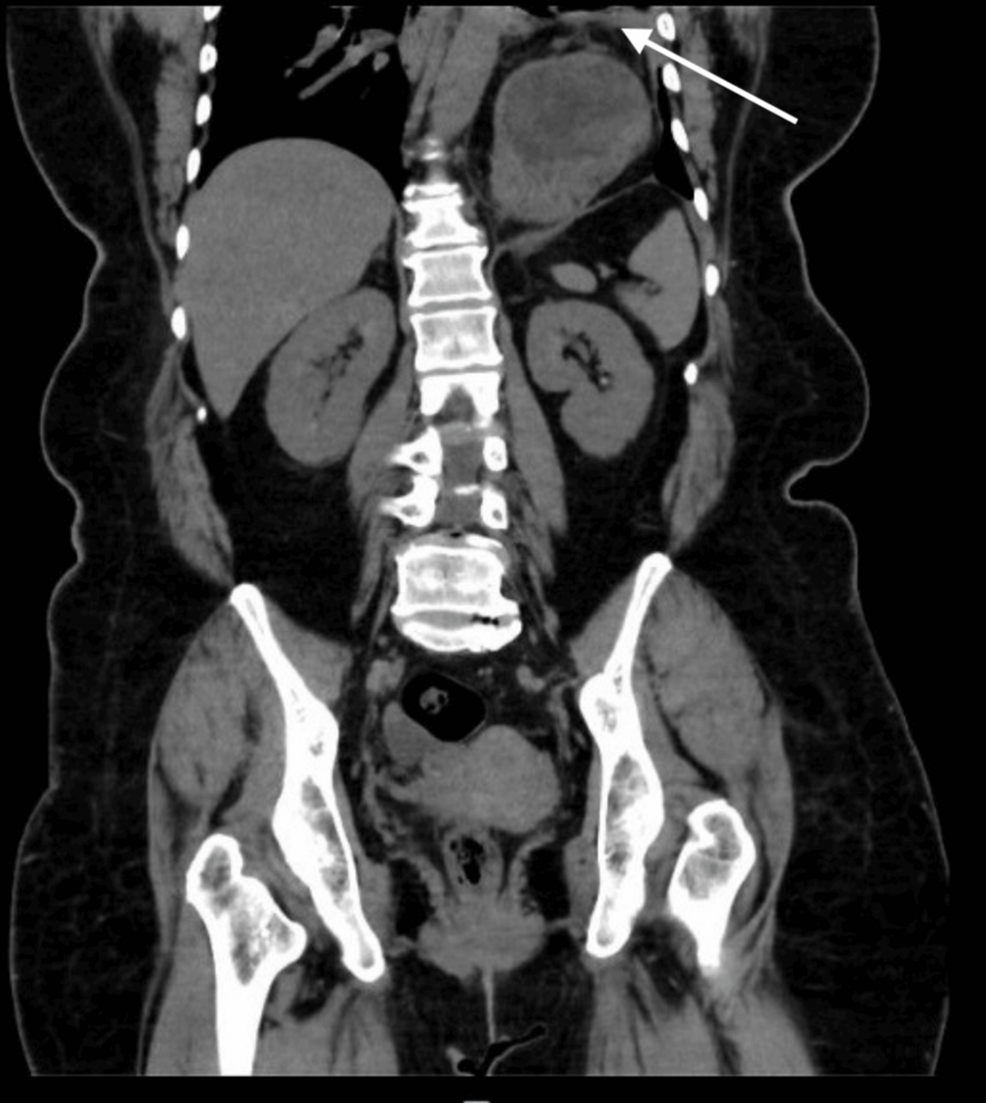
Medical imaging initially misinterpreted the condition as diaphragmatic eventration, an abnormal elevation of an attenuated hemidiaphragm without a true anatomical defect. A non-contrast abdominal computed tomography scan on June 19, 2026, showed an elevated gastric fundus, according to Cureus. A subsequent contrast-enhanced thoracic CT scan performed on June 26, 2026, revealed that part of the stomach had actually protruded into the left hemithorax through a true diaphragmatic defect.
Clinical Findings and Surgical Repair
Physical examination revealed decreased breath sounds and dull percussion over the left fourth intercostal space, where audible bowel sounds pointed toward abdominal viscera trapped in the chest. Cureus reported that the patient underwent a combined laparoscopic-thoracotomy repair after dense grade IV adhesions ruled out eventration.
Surgeons found a central defect in the left hemidiaphragm containing the stomach and omentum. Postoperative recovery involved mild subcutaneous emphysema that was managed conservatively, allowing the patient to leave the hospital on postoperative day five.
Why the hernia was misdiagnosed and how it was found
Why was the diaphragmatic hernia misdiagnosed initially?
The condition mimicked common gastrointestinal issues like dyspepsia and gastroesophageal reflux disease, and initial non-contrast CT scans misread the superiorly displaced stomach as diaphragmatic eventration.
What specific physical exam finding finally revealed the hernia?
Bedside auscultation detected bowel sounds, known as borborygmi, over the patient’s left fourth intercostal space, indicating that abdominal organs were inside the thoracic cavity.
How was the diaphragmatic defect treated?
The patient underwent a combined laparoscopic-thoracotomy surgical repair to address dense grade IV adhesions and safely return the protruding stomach and omentum to the abdomen.
Worth a look