Gastric Hemorrhage Reveals Primary Gastric Melanoma
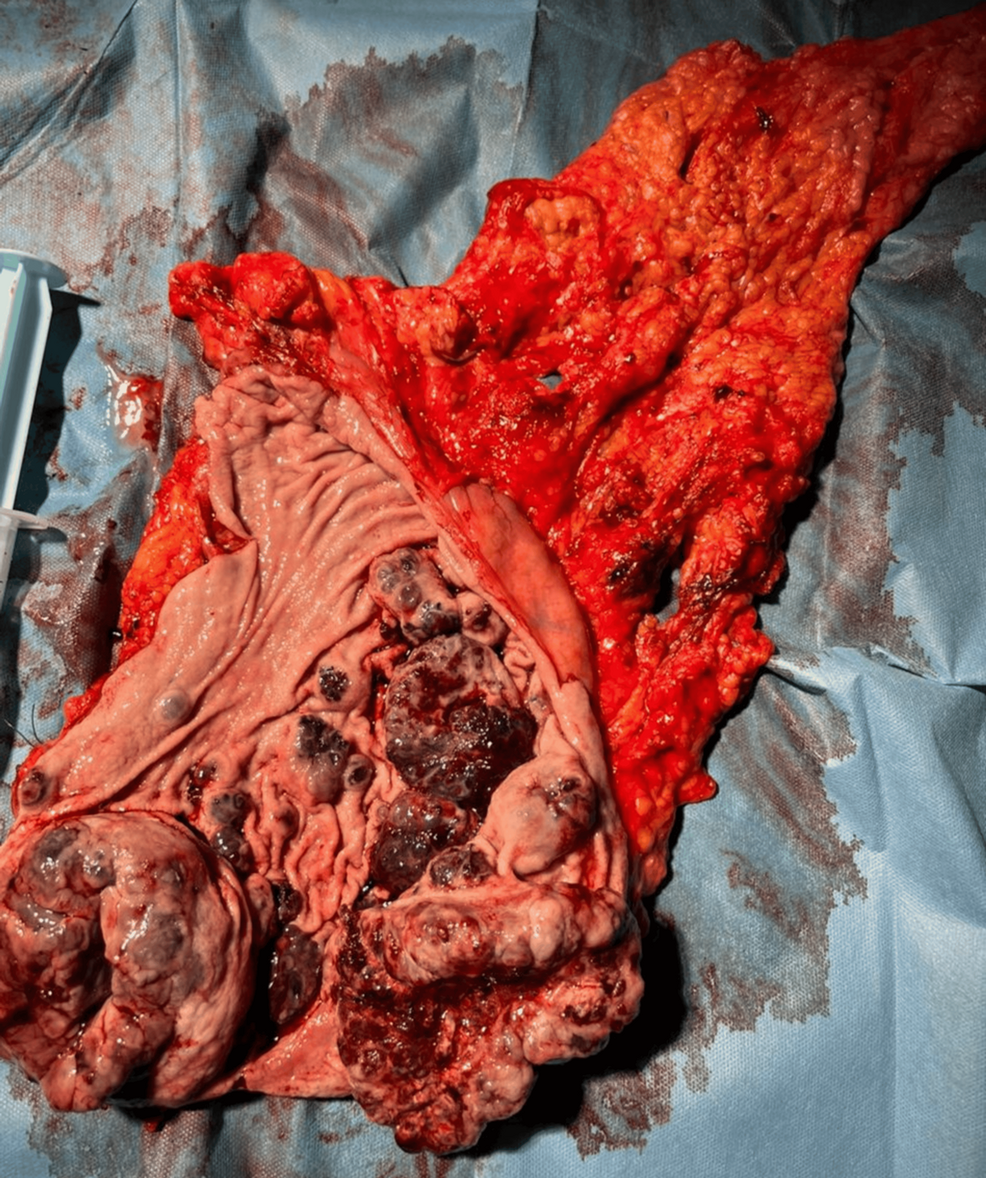
A 73-year-old man arrived at an emergency room exhibiting acute gastrointestinal bleeding symptoms, including melena, hematemesis, and severe abdominal pain, which ultimately led clinicians to diagnose a rare primary gastric melanoma, Cureus reported. While secondary gastrointestinal melanoma typically spreads from known cutaneous or ocular primary lesions, discovering a melanocytic tumor arising de novo in the stomach remains exceptionally rare. Initial endoscopy revealed irregular, dark, multifocal submucosal lesions across the gastric antrum, corpus, and fundus, prompting a total gastrectomy due to acute gastric hemorrhage.
Diagnostic Challenges in SOX10-Negative Melanoma
Macroscopic and microscopic examination of the resected stomach tissue revealed multilocular submucosal pigmented lesions extending through the entire wall into periventricular adipose tissue, alongside similar focal lesions in the omentum. Subsequent immunohistochemical analysis showed that the tumor cells tested positive for human melanoma black-45 (HMB-45), S100, vimentin, and CD56, but tested negative for SOX10. This negative SOX10 result is particularly notable because SOX10 usually serves as a highly sensitive nuclear marker for melanocytic differentiation, proving positive in nearly all typical melanocytic lesions. Pathologists emphasized that this case demonstrates how a negative SOX10 result does not automatically exclude melanoma when other morphology and melanocytic markers support the diagnosis.
Staging Evaluations and Subsequent Immunotherapy
Following the gastrectomy, contrast-enhanced computed tomography imaging of the chest, abdomen, and pelvis identified a pulmonary lesion sharing the exact same immunohistochemical profile as the gastric mass.
Contrasting Patient Presentations in Rare Medical Literature
Medical literature documents divergent presentations of primary gastric melanoma. While the 73-year-old male patient reported by Cureus presented with severe acute gastrointestinal hemorrhage and hematemesis, a separate case detailed in PMC described a 50-year-old male patient who presented with an asymptomatic drop in hemoglobin levels and generalized fatigue, discovered only after routine blood tests triggered a diagnostic upper gastrointestinal endoscopy that found a necrotic ulcerating lesion on the greater curvature of the stomach. That separate patient successfully underwent a subtotal gastrectomy with D2 lymphadenectomy yielding clear surgical margins, contrasting with the total gastrectomy required for the acute hemorrhage case.
Frequently Asked Questions About Primary Gastric Melanoma
Why is primary gastric melanoma considered so rare by physicians?
The stomach does not possess a resident population of normal melanocytes. True primary gastrointestinal melanoma is diagnosed only after healthcare providers thoroughly exclude all potential primary cutaneous, ocular, or mucosal skin sites.
How do clinicians diagnose gastric melanoma if SOX10 tests negative?
Pathologists rely on a broad immunohistochemical panel rather than a single marker. When markers such as HMB-45, S100, and vimentin test positive alongside supportive tumor morphology and extracellular pigmentation, clinicians can confirm the diagnosis despite a lack of SOX10 expression.
What treatment options are available for patients diagnosed with primary gastric melanoma?
Management typically follows protocols established for cutaneous melanoma, prioritizing surgical resection when feasible, such as total or subtotal gastrectomy. Unresectable or metastatic cases receive systemic therapies, including immune checkpoint inhibitors and targeted medications.